

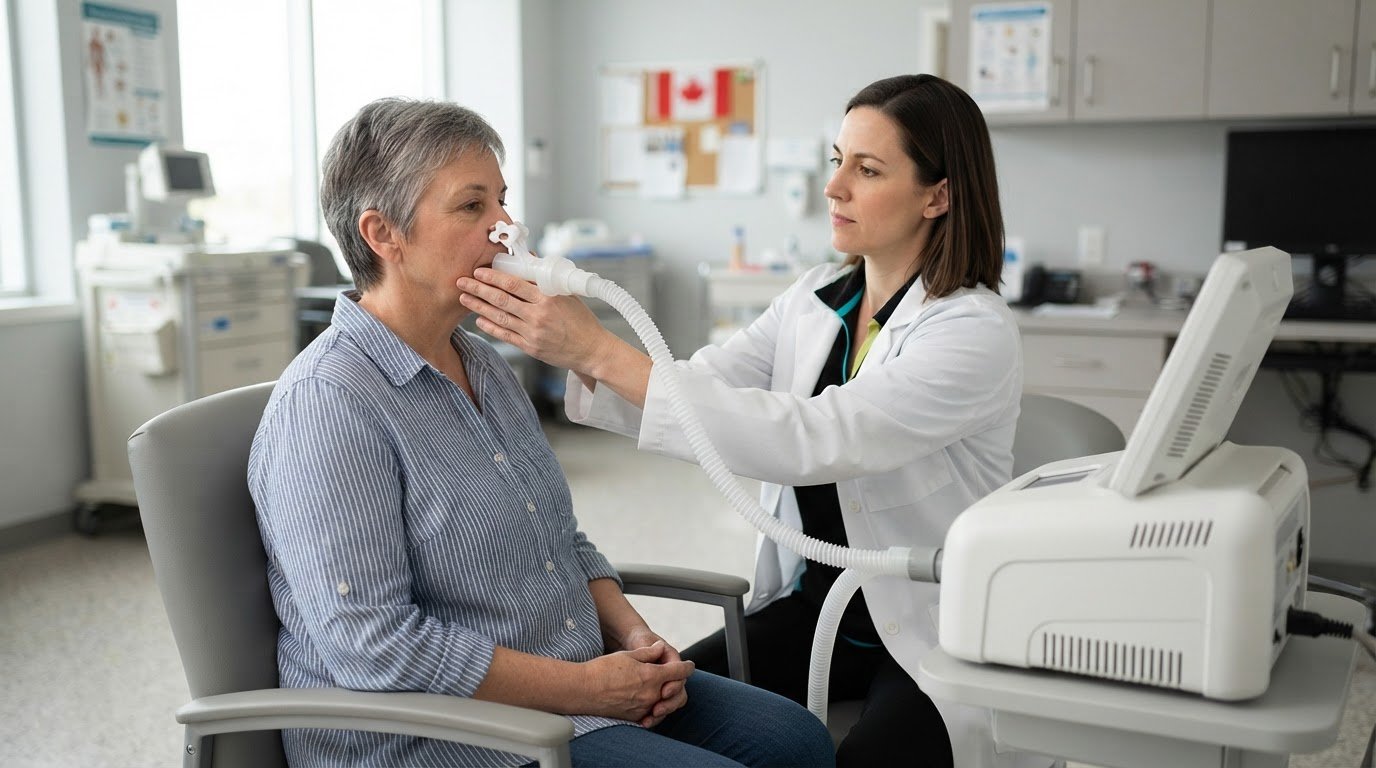
A spirometer with FeNO and oscillometry brings together three complementary views of airway function, not three versions of the same test. Spirometry measures how much air a patient can exhale and how quickly; FeNO assesses airway inflammation, while impulse oscillometry measures respiratory-system resistance and reactance during quiet breathing. Together, the results can add useful context when one test alone does not answer the clinical question.
It’s reasonable to expect spirometry to give a clear picture of asthma, but results can be normal between episodes. FeNO and oscillometry provide different information, helping clinicians interpret airflow findings alongside signs of inflammation and respiratory mechanics.
This article compares what each test measures, how the results can complement one another, and how the combination may fit into primary care. It also covers practical considerations for interpreting findings, helping respiratory care teams make informed pulmonary function testing decisions in Canada.
Key Takeaways
- Match each test to the clinical question: airflow and lung volumes, airway inflammation, or respiratory-system mechanics.
- Use oscillometry to add information about airway resistance and reactance during quiet breathing, particularly when forced manoeuvres provide limited insight.
- Interpret FeNO alongside spirometry findings and the clinical picture; each test measures a different aspect of airway function.
- Distinguish pulmonary diagnostics from respiratory support equipment: LungFit® PH is an option to explore when inhaled nitric oxide delivery is the relevant clinical need.
Impulse oscillometry (IOS) as a complement to spirometry
Oscillometry adds information about respiratory mechanics to spirometry and FeNO findings. Because each test assesses a different aspect of airway function, results are interpreted together, not as interchangeable measurements.
Differences Among the Tests
Spirometry measures exhaled airflow, FeNO measures nitric oxide in breath, and IOS assesses respiratory-system resistance and reactance during quiet breathing. That distinction matters in asthma assessment: spirometry may be normal between episodes, while FeNO can indicate active airway inflammation. According to the National Library of Medicine, IOS can distinguish small-airway from large-airway obstruction and may be more sensitive to peripheral airway disease than spirometry.
Accuracy of Combined Devices
A combined device does not automatically make results more accurate than standalone testing. Each measurement must be performed and interpreted using its own method, with technique and reference values taken into account. Spirometry, for example, depends on a suitable forced manoeuvre, while oscillometry records responses during quiet breathing. Assess each measurement’s accuracy separately: integration describes how tests are brought together, not a shared accuracy rating.
Systems Combining Three Tests
ALDS PRO by Lothar Medical combines oscillometry, spirometry, and FeNO in one integrated system, with cloud-based reporting. This answers the practical equipment question: the system offers all three measurements, rather than requiring separate devices for each. In Canada, licensing applies to the specific medical device; confirm the exact model’s status in Health Canada’s licensing records when planning procurement.
Conditions Assessed
FeNO and oscillometry can contribute information to an asthma assessment, including about airway inflammation and respiratory mechanics. Neither test establishes a diagnosis on its own. Preparation depends on the test and clinic protocol. Patients should follow medication instructions and avoid changing prescribed treatment independently. Spirometry requires a forced exhalation, while oscillometry uses quiet breathing. Poor technique, coughing, or an inadequate mouth seal can affect measurements, so clinicians interpret findings in context.
Fractional exhaled nitric oxide (FeNO)
Fractional exhaled nitric oxide testing measures nitric oxide in a patient’s breath and reports the result in parts per billion (ppb). It provides information about airway inflammation at the time of assessment, rather than directly measuring airflow or lung volume. In primary care, this distinction helps respiratory teams interpret FeNO alongside spirometry and symptoms, instead of treating one reading as a complete asthma assessment.
FeNO can help identify active airway inflammation, possible non-adherence to inhaled corticosteroids, and early signs of flare-ups. Most patients aged five years and above can complete the test. Interpret results in context: treatment can affect readings, and FeNO answers a different question from a forced expiratory manoeuvre. For clinicians, it is a complementary marker when assessing asthma diagnosis and treatment response.
Research findings illustrate how readings can vary across groups and over time. One study reported baseline FeNO levels of 78 ppb in preschoolers and 58 ppb in school-age children or adolescents. Three months after ICS-LABA treatment began, FeNO changed by -46% and -14%, respectively. Those figures describe the study groups, not a threshold for an individual patient. They show why clinicians consider age, treatment, and other findings when interpreting results.
FeNO also provides information that oscillometry does not: nitric oxide concentration in exhaled breath. Conversely, FeNO alone does not characterize respiratory-system resistance or reactance. Read together with spirometry and IOS, it can help distinguish inflammatory signals from airflow or mechanical findings. For clinics assessing their testing needs, FeNO testing equipment can be considered as part of a broader pulmonary function testing setup, with the intended patient population and clinical workflow guiding equipment selection.
The webinar examines how fractional exhaled nitric oxide (FeNO) can improve asthma diagnosis and treatment. The median fraction of exhaled nitric oxide among study participants was 19.0 ppb.
In the study, the change in predicted FEV1 was significantly positively correlated with FENO (P =.009). In participants whose peripheral blood eosinophil percentage could be measured, FENO was significantly associated with that percentage (P =.001). The study therefore reported associations involving both predicted FEV1 change and peripheral blood eosinophil percentage.

IOS measures of airway resistance and reactance
Impulse oscillometry (IOS) measures respiratory-system mechanics while patients breathe quietly. A device applies small pressure oscillations at the mouth and records the response. The U.S. National Library of Medicine describes this method as assessing respiratory-system properties without requiring a forced exhalation. Resistance describes opposition to airflow, while reactance reflects the respiratory system’s elastic and inertial behaviour. Together, these measurements add functional information beyond the volume and flow values obtained through spirometry.
Common IOS measures include R5, R20, R5-R20, Xrs, and AX. R5 reflects resistance across the respiratory system, while R20 is more closely associated with larger airways; their difference, R5-R20, can indicate peripheral airway dysfunction. Xrs represents reactance, and AX is the area under the reactance curve. According to the National Library of Medicine, oscillometry can help distinguish small-airway from large-airway obstruction. It may therefore add insight when assessing patients with asthma, including when spirometry does not explain symptoms.
Study findings show why clinicians interpret specific IOS measures rather than relying on one value. In a severe-asthma clinic study covering January 2019 to December 2022, small-airway dysfunction prevalence ranged from 53% to 78%, depending on the oscillometry parameter. Dysfunction defined by R5-R20 was associated with increased exacerbation risk, with an odds ratio of 2.60; AX-defined dysfunction had an odds ratio of 2.31. These associations describe the study group and do not predict an individual patient’s outcome.
Control measures also differed by IOS parameter. In that clinic study, R5-R20 was associated with poor control defined by an ACQ6 score greater than 1.5, with an odds ratio of 2.97; it was also associated with poor control defined by an ACT score below 20, with an odds ratio of 2.44. Clinicians interpret resistance and reactance alongside symptoms, spirometry, and exhaled nitric oxide, since each measure addresses a different aspect of airway function.
FeNO and spirometry in primary care
Primary care testing can pair spirometry’s lung function measurements with FeNO’s indication of airway inflammation. Spirometry records how much air a patient can exhale and how quickly, including forced expiratory volume in one second (FEV1), forced vital capacity (FVC), and the FEV1/FVC ratio. FeNO measures nitric oxide in exhaled breath, adding a different clinical signal to an asthma assessment.
This distinction matters because spirometry can be normal between asthma episodes. A normal result at one appointment does not provide the same information as FeNO, which can help show whether airway inflammation is active at the time of assessment. For example, when airflow measurements are normal but FeNO is elevated, a clinician has two different findings to consider, rather than a single result that settles the question.
FeNO can also inform follow-up. It may help identify non-adherence to inhaled corticosteroids or detect flare-ups early, while spirometry tracks airflow and lung function. Most patients aged five years and above can complete FeNO testing. These measures are most useful alongside symptoms, medication history, and the reason for testing. FeNO does not replace spirometry, and spirometry alone does not measure airway inflammation.
In primary care, the clinical question should guide test selection and interpretation. For suspected asthma, spirometry can assess airflow obstruction, while FeNO contributes information about inflammation. If spirometry is normal but symptoms remain relevant, FeNO provides another type of evidence for clinical assessment. Results support the assessment of airway disease, but must be interpreted in context rather than treated as a diagnosis on their own.
Clinics planning pulmonary function testing can consider whether their equipment supports the measurements required by their patient population and workflow. Explore Lothar Medical spirometry as part of planning spirometry capacity for primary care assessment.
Spirometry readings used to assess airflow include FEV1, FVC and the FEV1/FVC ratio. FeNO provides separate information about airway inflammation, so these measures should not be treated as interchangeable. Considering each result in relation to the clinical question, symptoms and medication history keeps the assessment grounded in the reason for testing and the information each measure provides.
Novus Medical: LungFit® PH
LungFit® PH is an inhaled nitric oxide system offered by Novus Medical for facilities considering respiratory support equipment. It uses patented Plasma Pulse Technology® to generate inhaled nitric oxide from ambient air; it does not measure FeNO or perform spirometry or oscillometry.
This distinction matters in clinical planning: FeNO testing measures nitric oxide in exhaled breath, while LungFit® PH is a separate respiratory therapy system. Consider LungFit® PH when the clinical need is inhaled nitric oxide delivery, not when selecting equipment to assess airway inflammation or lung function. Matching equipment to its intended role helps keep diagnostic testing and respiratory support workflows clear.
For Canadian care teams evaluating these categories, Novus Medical offers LungFit® PH alongside pulmonary diagnostic equipment. Contact Novus Medical or visit novusmedical.ca to discuss the LungFit® PH system.
Plan the next step for your clinic
Before selecting equipment, define the clinical questions your team needs testing to answer and how results will fit into existing workflows. A spirometer with FeNO and oscillometry can bring different assessment capabilities together, but the choice should reflect the measurements required, patient population, and staff workflow. Match those needs to the devices’ intended functions, keeping diagnostic testing distinct from respiratory therapy.
Novus Medical offers Lothar Medical spirometry, FeNO, and oscillometry equipment for pulmonary diagnostics. For separate respiratory-care needs, its offerings also include LungFit® PH and the EO-150 Ventilator, as well as the MagVenture Accelerator Training Program. These products address distinct clinical and training requirements, rather than serving as substitutes for pulmonary function testing.
Discuss your clinic’s priorities with Novus Medical to identify a practical direction for equipment planning. Contact Novus Medical to discuss testing and take the next step with clarity and confidence.
Frequently Asked Questions
What is a spirometer with FeNO and oscillometry testing?
A spirometer with FeNO and oscillometry combines three pulmonary measurements in one system. Novus Medical offers ALDS PRO by Lothar Medical, an integrated system that provides spirometry, FeNO, and oscillometry with cloud-based reporting. For clinics comparing equipment, it can bring results into a shared workflow, while clinicians select the measurements suited to each assessment.
What preparation is required before spirometry, FeNO, and oscillometry tests?
Preparation depends on the test and clinic protocol. Follow medication instructions and do not change prescribed treatment independently. Spirometry requires a forced exhalation, while oscillometry uses quiet breathing.
Disclaimer
Disclaimer: Articles on this website are produced with the assistance of automated content tools (AutoSEO) and are intended solely for general informational purposes. This content does not constitute professional advice. While we strive to maintain accurate and up-to-date information, readers should verify key details independently before taking action based on any content found on this site.

Leave a Reply
Your email is safe with us.